Posts

Bimonthly assessment ( February)

Image
Questions: 1)50 year man, he presented with the complaints of Frequently walking into objects along with frequent falls since 1.5 years Drooping of eyelids since 1.5 years Involuntary movements of hands since 1.5 years  Talking to self since 1.5 years  https://archanareddy07.blogspot.com/2021/02/50m-with-parkinsonism.html?m=1 a). What is the problem representation of this patient and what is the anatomical localization for his current problem based on the clinical findings? A)chronic smoker and  tobacco chewer H/o left lower limb fracture 2 years back Started 15 years ago, initially chewed 1 or 2 packs/day & gradually increased to 3-4/day and even 5-7 on a few days. Abruptly stopped consuming both alcohol & khaini after the RTA in June, 2018. Son has offered khaini several times after, but the patient was very reluctant eversince. Now presenting complaints are frequently walking into objects along with frequent falls since, Drooping of eyelids(progressing as the d...

60yr female with shortness of breath

Image
A 60yr female who was farmer by occupation came with the complaints of Shortness of breath since 1o clock in the night .. HOPI: pt was apparently asymptomatic since 1  o clock in the night ..then started developing sudden onset breathlessness in the night which was grade 4 , progressive .pt was taken to the local RMP ,found to have high BP levels and took some medication and came to KIMS for further evaluation. Past history: K/C/O DM and HTN  since 10 years . Persoal history: PICKLE : negative.   General examination : Pt conscious but irritable . Vitals : BP : 180/90 mmHg             PR: 140bpm             CVS: S1S2 +              RS: BAE + , Coarse crepts in all areas.             P/A: Soft.            GRBS: 256mg/dl Investigations: Diagnosis: INFERIOR WALL NSTEMI with CARDIAC ASTHMA...

Medicine paper for January 2021

Image
a)  Problem representation : 26yr old female with k/c/o SLE Polyarthritis with head ache since 8 days and fever, vomtings since 4 days and altered sensorium since 2 days with Euvolemic hyponatremia under evaluation. Anatomical localization: Brain. b) etiology: CVA , TB Meningitis , SLE vasculitis ,SIADH secondary to infection.   Initially the first on-call team thought it was Hyponatremia that is secondary to SIADH which is causing altered sensorium.. and also MRI was done which showed stroke the second on call team with further work up decided to do LP which showed the CSF positive for CBNAAT...thus came to the diagnosis of TB Meningitis. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5357611/( Bisphosphonate prophylaxis). https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3970554/(proton pump for corticosteroid ulcers) https://pubmed.ncbi.nlm.nih.gov/10067053/ ( TB Meningitis in SLE pts) C) Bisphosphonates were given to prevent osteoporotic fracture risk associated ...

Bimonthly internal assessment

Image
DECEMBER ASSESSMENT:  "This is my submission for the Bimonthly internal assessment for the month of November." Most of the information here have been collected from different reference sites, the links to which have been mentioned. The points copy pasted have been put in quotes.  The questions to the cases being discussed can be viewed from the link below 👇 https://medicinedepartment.blogspot.com/2020/12/medicine-question-paper-for-december.html?m=1 1) A 55 year old man with Recurrent Focal Seizures Detailed patient case report here:  http://ushaindurthi. blogspot.com/2020/11/55-year- old-male-with-complaints-of. html 1. What is the problem representation of this patient and what could be the anatomical site of lesion ? Ans :  55 year old man presented to the casualty with the complaints of Unable to move his right upper limb he suddenly started complaining that he couldn’t move his right upper limb few minutes later he developed a sudden onset, tonic clonic seizure...

60 yr male CKD on MHD

Image
Past history : k/c/o DM since 10years and on Medication ( given by Government ) K/C/O HTN since 7 years and on medication.  Personal history :  PERSONAL HISTORY: Mixed diet, Appetite normal,   alcoholic(30ml/day) and Smoking 36beedis per day.  No  other addictions. GENERAL EXAMINATION: Patient was consious, coherent, cooperative;oriented to time,place,person. Pallor present  No icterus, clubbing, cynosis, lypmhadenopathy. Bilateral pedal edema present.  Investigations: Treatment: 1) Inj. Lasix 40mg /IV /BD.  2)Tab.clinidipine 10 mg /PO/ OD.  3) inj. Human actrapid insulin /SC.  4) tab. Nodosis 500mg PO/TID . 5) Tab. Shelcal CT 500mg/OD 6) Tab. Alfa D3/ PO/OD. 7) Tab. Orofer XT PO/OD. 8) Inj Ceftriaxone 1gm IV/BD. 9) Inj.Erythropoietin 4000IU /S...

Blended learning bimonthly assessment for November 2020

Image
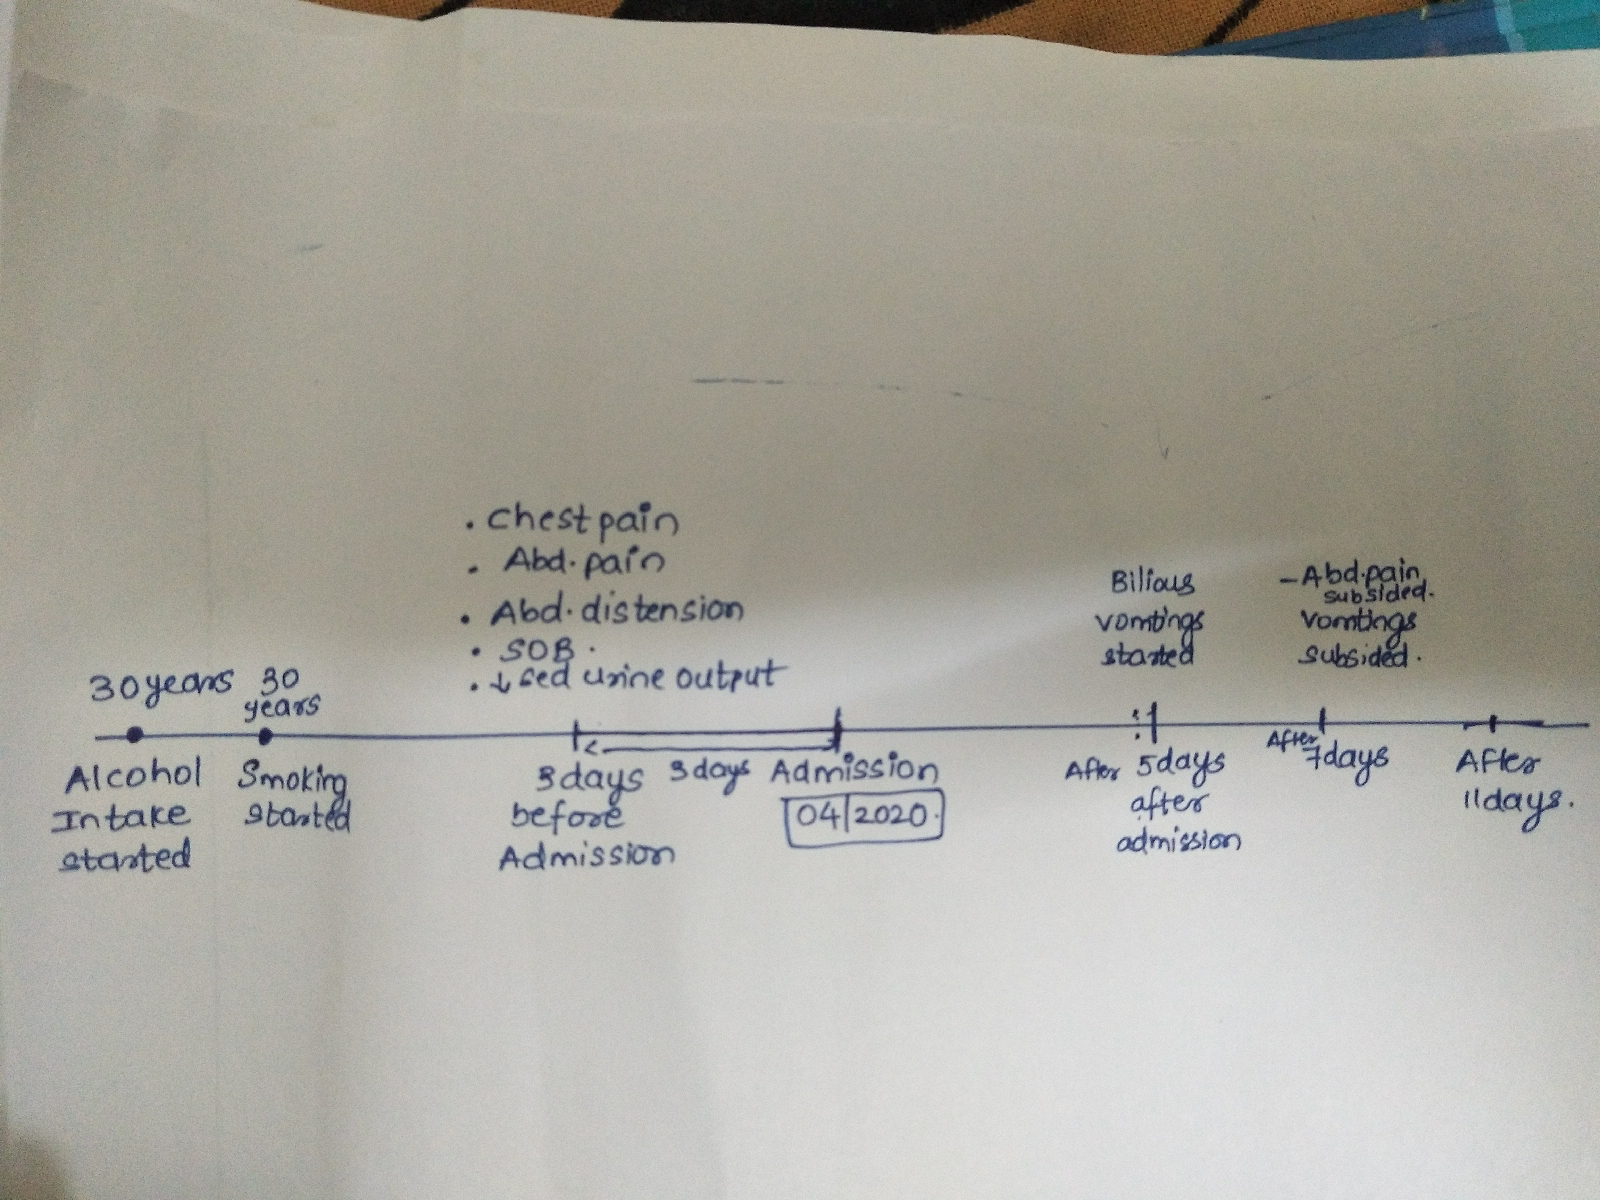
Question 1) pain in the epigastric region differentials Inferior wall MI(normal ecg and echo) Acute pancreatitis(radiation to the back)-usg finding and elevated serum amylase level Perforated peptic ulcer  Causes of acute pancreatitis- harrison pg no 2348 Gall stones : https://gi.org/topics/gallstone-pancreatitis/ This occurs at the level of the sphincter of Oddi, a round muscle located at the opening of the bile duct into the small intestine. If a stone from the gallbladder should travel down the common bile duct and get stuck at the sphincter, it blocks outflow of all material from the liver and pancreas. This results in inflammation of the pancreas that can be quite severe. 2)sob- acidosis due to renal failure          ? Ards secondary to sepsis/pancreatitis           Pleural effusion due to acute pancreatitis            3)decreased urine output-pre renal Aki secondary to volume loss(oliguric) 3rd sp...

A 55yr old male with Chronic kidney disease and Hypertension

Image
A 55yr old male sandibatla Chief complaints : complaining of Pedal edema  and shortness of breath since 10 days and fever since 15 days.  HOPI: Pt was apparently asymptomatic 15 days back and then developed fever which was intermittent, not associated with chills and rigors.. relieving with medication.. After 4 days patient started developing pedal edema up to ankles,  which was progressive and Associated with Shortness of breath.. Then pt went to the local doctor where his creatinine was found to be 8.5 and patient was referred to kims for further evaluation.  Past history : k/c/o DM and on Insulin Mixtard 20 and 15 units and  K/C/O HTN since 5 years and on Atenolol 50 mg  Personal history :  PERSONAL HISTORY: Mixed diet, Appetite normal, Occasionally  alcoholic and Smoking 3 beedis per day.  No  other addictions. GENERAL EXAMINATION: Patient was consious, coherent, cooperative;oriented to time,place,person. Pallor present  No icte...